PROXIMAL HUMERUS FIXATION
This leaflet provides general information to help you understand surgery to fix a proximal humerus (upper arm) fracture.
Realigning and holding the broken upper arm bone so the shoulder can heal and move.
At the heart of my practice is Shared Decision-Making. Whether we pursue conservative management (Plan A) or surgical intervention (Plan B), the goal is to create a tailored treatment plan that aligns with your lifestyle, values, and functional goals.


This leaflet provides general information and does not replace individual medical advice.
Watch the Surgery Videos
For more information you can watch procedure videos at: www.youtube.com/c/ProfBijayendraSingh
Watch on YouTubeThe Anatomy of the Shoulder Joint
The shoulder is one of the most complex joints in the body, relying on several structures working together:
How the Shoulder Works
Three main bones form the joint:
- Humerus (upper arm bone)
- Clavicle (collarbone)
- Scapula (shoulder blade)
The Four Key Joints
- Glenohumeral Joint – the main ball-and-socket joint
- Acromioclavicular (AC) Joint – collarbone meets shoulder blade
- Subacromial Space – tunnel above the rotator cuff
- Scapulothoracic Joint – shoulder blade glides over rib cage
The Labrum (Stabilising Ring)
- A rim of rubbery tissue that deepens the shallow shoulder socket — like a "bumper" or suction cup that keeps the joint stable and prevents dislocation.
The Rotator Cuff
Four deep muscles keep the ball centred in the socket and let you lift and rotate your arm:
- Supraspinatus
- Infraspinatus
- Subscapularis
- Teres Minor

About the Operation
Most proximal humerus fractures heal without surgery. Fixation is offered when the fracture is significantly displaced, splits the ball of the joint, or is at risk of not healing well. The fragments are realigned and held with a plate and screws (sometimes a rod); in selected cases a reverse shoulder replacement is a better option.
Benefits & Logic
The operation aims to:
- Restore the normal alignment of the broken bone
- Hold the fracture stable so it heals correctly
- Allow earlier movement and reduce the risk of deformity
- Tailored treatment based on fracture pattern, bone quality and patient needs
The Procedure, Step by Step
The operation, step by step:
- Incision: made on the front or side of the shoulder
- Realignment: the bone fragments are put back in position
- Fixation: a plate and screws (or a rod) hold the bone
- Bone graft if required
- Closure: dissolvable stitches, a dressing and a sling
Before, During & After Surgery
Before Surgery
- Fasting: no food for 6 hours, no drinks for 2 hours before
- Smoking: avoid for at least 12 hours before, to aid healing
- Medications: continue as advised by the pre-op team
On the Day
- Admission: check in at main reception, then to your room
- Consultation: meet your surgeon and anaesthetist
- Preparation: timing and instructions are reviewed
Anaesthesia
- General anaesthetic with a nerve block that numbs the arm
- Nerve block alone (awake) if general anaesthetic is unsuitable
Recovery & Results
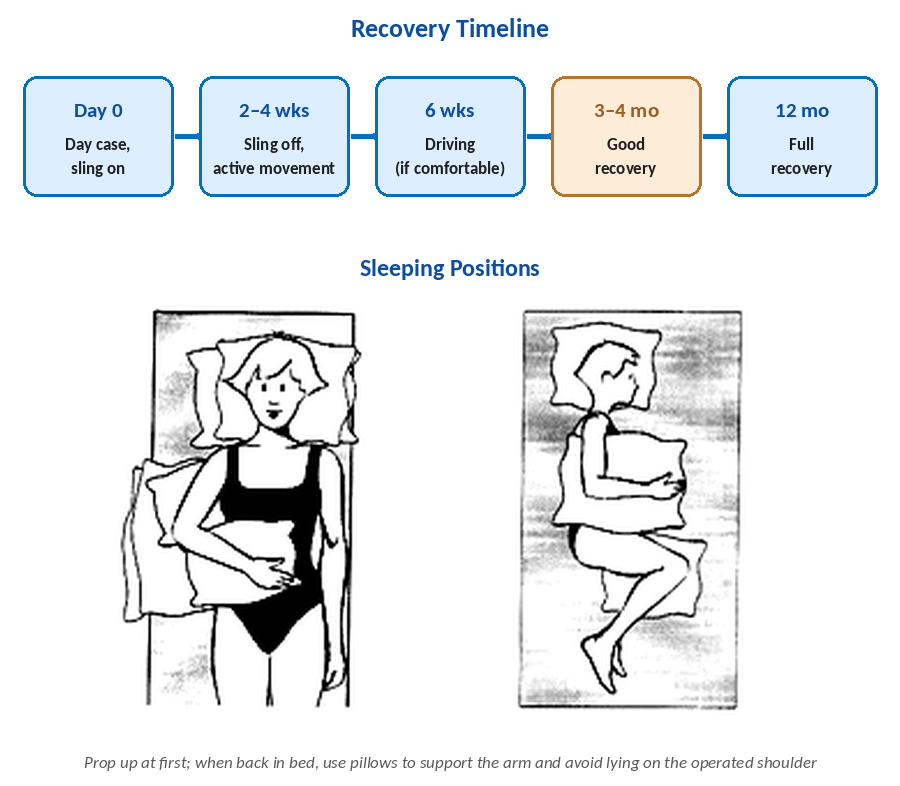
Recovery is a partnership. The timeline below is a guide — your physiotherapist and I will adapt it to you — this shared decision-making process ensures you are fully informed and involved in your care.
Recovery Milestones
- Sling: usually worn for 2–3 weeks
- Gentle exercises: begin from a few days after surgery
- Recovery: most do well by 3–4 months
- Bone healing: usually complete by around 3–6 months
Results
Fixation restores alignment and allows early movement. In older patients with soft bone or a split ball, a reverse replacement may give a more reliable result.
After Surgery — In the First Weeks
- Stay: most patients go home the same day
- Sling: usually worn for 2–3 weeks to protect the repair
- Pain Relief: start at home; take regularly for the first few days
- Wound Care: dressings changed at 24–48 hours; showering after 3–5 days
- Physiotherapy: early gentle movement is important to avoid stiffness
- Follow Up: 2–6 weeks post op to monitor progress
Risks & Complications
Uncommon, but possible:
- Anaesthetic: complications are rare
- Infection: fewer than 1 in 100; treated with antibiotics
- Stiffness: common; early physiotherapy reduces it
- Blood Supply: rarely the ball loses its blood supply and collapses over time
- Fixation / Failure: screws can cut out in soft bone; occasionally revision is needed
- Delayed / Non-Union: fracture may be slow to heal or fail to heal, may require further treatment or surgery
- Malunion: may heal in less-than-ideal position and can lead to stiffness and altered function; may require corrective surgery
Return to Activities
This can be extremely variable and discuss with the surgeon. These are just guidelines.
Desk work 2–4 weeks; Driving: once safe and out of the sling, usually 4–6 weeks; Manual Work: 6–12 weeks; Golf: 12–16 weeks. Sport is staged — your physiotherapist will guide the timeline. A member of the team will discuss your specific plan.
Recovery Timeline & Sleeping
⚠ Red Flags — When to Seek Urgent Help
Numbness or a cold hand, skin at risk over the fracture, or fever and wound discharge — seek urgent assessment.
If you experience any of the above, contact the practice, your GP, NHS 111, or attend your nearest Emergency Department.
Key Points to Remember
- Used for displaced or unstable fractures
- A plate and screws hold the bone to heal
- Early movement helps avoid stiffness
- A replacement is sometimes the better option
Questions You May Wish to Ask
- When can I take the sling off?
- When can I drive and return to work?
- How much improvement can I expect?
- What happens if I don't have surgery?
Book or Enquire Directly at Each Site
| LIPS Healthcare London | 0203 870 9996 | singh.admin@lips.org.uk |
| Spire Alexandra Chatham | 01634 662866 | alexandraselfpaypsc@spirehealthcare.com |
| Practice Plus Gillingham | 01634 969045 | Private.gillingham@practiceplusgroup.com |