SLAP REPAIR
This leaflet provides general information to help you understand arthroscopic SLAP repair for a torn labrum at the top of the socket.
This keyhole procedure re-attaches the torn labrum to restore stability, and is usually a day case.
At the heart of my practice is Shared Decision-Making. Whether we pursue conservative management (Plan A) or surgical intervention (Plan B), the goal is to create a tailored treatment plan that aligns with your lifestyle, values, and functional goals.
Watch the Surgery Videos
For more information you can watch procedure videos at: www.youtube.com/c/ProfBijayendraSingh
Watch on YouTubeThis leaflet provides general information and does not replace individual medical advice.
The Anatomy of the Shoulder Joint
The shoulder is one of the most complex joints in the body, relying on several structures working together:
How the Shoulder Works
Three main bones form the joint:
- Humerus (upper arm bone)
- Clavicle (collarbone)
- Scapula (shoulder blade)
The Four Key Joints
- Glenohumeral Joint – the main ball-and-socket joint
- Acromioclavicular (AC) Joint – collarbone meets shoulder blade
- Subacromial Space – tunnel above the rotator cuff
- Scapulothoracic Joint – shoulder blade glides over rib cage
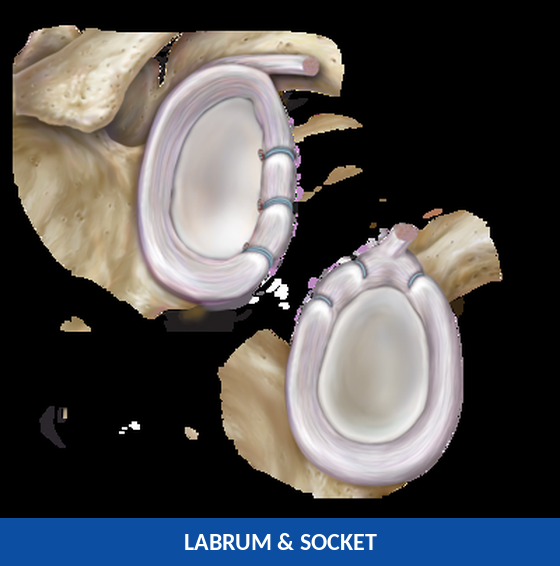
The Labrum (Stabilising Ring)
- A rim of rubbery tissue that deepens the shallow shoulder socket — like a "bumper" or suction cup that keeps the joint stable and prevents dislocation.
The Rotator Cuff
Four deep muscles keep the ball centred in the socket and let you lift and rotate your arm:
- Supraspinatus
- Infraspinatus
- Subscapularis
- Teres Minor

About the Operation
A SLAP repair re-attaches the torn top of the labrum — where the biceps anchors — back onto the socket. By keyhole surgery, the torn labrum and socket edge are prepared and secured with small anchors and stitches. In some patients, a biceps tenotomy or tenodesis is a better option than repair, and this is discussed with you.
Benefits & Logic
The operation aims to:
- Relieve pain from the torn labrum
- Restore the normal attachment and stability
- Prevent further catching, locking or instability
- Joint assessment
- Minimally invasive keyhole surgery with a smaller scar and more predictable recovery
The Procedure, Step by Step
The operation, step by step:
- Assessment: a camera examines the joint and confirms the tear
- Preparation: the torn labrum and socket edge are prepared
- Repair: anchors and stitches re-attach the labrum
- If necessary, biceps tenodesis is performed (additional or alternative)
- Other issues such as a loose fragment or damaged cartilage are addressed
- Closure: dissolvable stitches and a sling
Before, During & After Surgery
Before Surgery
- Fasting: no food for 6 hours, no drinks for 2 hours before
- Smoking: avoid for at least 12 hours before, to aid healing
- Medications: continue as advised by the pre-op team
- Please read 'Preparing for Surgery'
On the Day
- Admission: check in at main reception, then to your room
- Consultation: meet your surgeon and anaesthetist
- Preparation: timing and instructions are reviewed
Anaesthesia
- General anaesthetic with a nerve block that numbs the arm
- Nerve block alone (awake) if general anaesthetic is unsuitable
Recovery & Results
Recovery is a partnership. The timeline below is a guide — your physiotherapist and I will adapt it to you — this shared decision-making process ensures you are fully informed and involved in your care.
Recovery Milestones
- Sling: usually worn for a few weeks
- Gentle exercises: begin as advised
- Recovery: most do well by 3–4 months
- Return to sport: often around 4–6 months
Results
Most patients get good pain relief and a stable shoulder. Where repair is not ideal, a biceps tenodesis gives reliable results.
After Surgery — In the First Weeks
- Sling: worn for a few weeks to protect the repair
- Pain Relief: start at home; take regularly for the first few days
- Wound Care: dressings changed at 24–48 hours; showering after 3–5 days
- Physiotherapy: a graded programme; avoid heavy biceps loading early
- Follow Up: 2–6 weeks post op to monitor progress
Risks & Complications
Uncommon, but possible:
- Anaesthetic: complications are rare
- Infection: fewer than 1 in 1000; treated with antibiotics
- Stiffness: some stiffness can occur, usually improves with physiotherapy
- Persistent Pain: a small number have ongoing pain, sometimes needing tenodesis
- Nerve: minor, temporary irritation in about 5%
- Failure of Repair: 80–85% achieve good / excellent recovery; some may need further investigation / intervention
Return to Activities
This can be extremely variable and discuss with the surgeon. These are just guidelines.
Desk work 2–4 weeks; Driving: once safe and out of the sling, usually 4–6 weeks; Manual Work: 6–12 weeks; Golf: 12–16 weeks. Sport is staged — your physiotherapist will guide the timeline. A member of the team will discuss your specific plan.
Recovery Timeline & Sleeping

⚠ Red Flags — When to Seek Urgent Help
Fever, spreading redness or discharge from the wound, worsening pain, or numbness and a cold hand — seek urgent assessment.
If you experience any of the above, contact the practice, your GP, NHS 111, or attend your nearest Emergency Department.
Key Points to Remember
- Re-attaches the torn top of the labrum
- Symptoms matter more than the scan
- Usually a day case
- Sometimes a biceps tenodesis is the better option
Questions You May Wish to Ask
- When can I take the sling off?
- When can I drive and return to work?
- How much improvement can I expect?
- What happens if I don't have surgery?
Book or Enquire Directly at Each Site
| LIPS Healthcare London | 0203 870 9996 | singh.admin@lips.org.uk |
| Spire Alexandra Chatham | 01634 662866 | alexandraselfpaypsc@spirehealthcare.com |
| Practice Plus Gillingham | 01634 969045 | Private.gillingham@practiceplusgroup.com |