DISTAL CLAVICLE OSTEOLYSIS (DCO) — "WEIGHT-LIFTER'S SHOULDER"
This leaflet provides general information to help you understand distal clavicle osteolysis (DCO) and the available treatment options.
Not everyone with DCO needs surgery.
At the heart of my practice is Shared Decision-Making. Whether we pursue conservative management (Plan A) or surgical intervention (Plan B), the goal is to create a tailored treatment plan that aligns with your lifestyle, values, and functional goals.
This leaflet provides general information and does not replace individual medical advice.
The Anatomy of the Shoulder Joint
The shoulder is one of the most complex joints in the body, relying on several structures working together.
How the Shoulder Works
Three main bones form the joint:
- Humerus (upper arm bone)
- Clavicle (collarbone)
- Scapula (shoulder blade)
The Four Key Joints
- Glenohumeral Joint – the main ball-and-socket joint
- Acromioclavicular (AC) Joint – collarbone meets shoulder blade
- Subacromial Space – tunnel above the rotator cuff
- Scapulothoracic Joint – shoulder blade glides over rib cage
The "Cushioning" (Articular Cartilage)
A smooth, slippery coating on the ball and socket surfaces that lets the bones glide over each other without friction, for pain-free movement.
The Labrum (Stabilising Ring)
A rim of rubbery tissue that deepens the shallow shoulder socket — like a "bumper" or suction cup that keeps the joint stable and prevents dislocation.
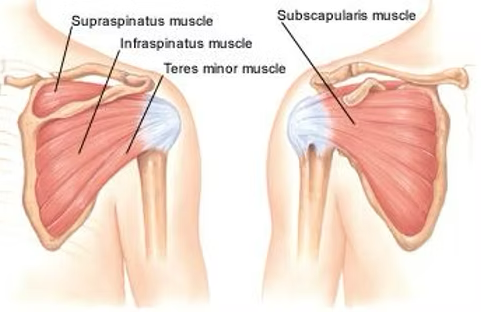
The Rotator Cuff
Four deep muscles keep the ball centred in the socket and let you lift and rotate your arm:
- Supraspinatus
- Infraspinatus
- Subscapularis
- Teres Minor
What Is Distal Clavicle Osteolysis?
Distal clavicle osteolysis (DCO) is an uncommon condition in which the outer end of the collarbone suffers repeated micro-stress injuries. Bone is eroded faster than it can repair, leading to gradual bone loss at the AC joint — most often in weight-trainers under 40.
Who Gets It?
Most common under 40, in:
- Weightlifting and gym training
- Rugby and martial arts
- Construction, plastering and overhead work
What Causes It?
An overuse process at the outer clavicle:
- Repetitive overhead lifting or load
- Micro-stress fractures of the outer clavicle
- Bone eroded faster than it can repair
- Symptoms similar to ACJ arthritis
Symptoms & Examination
Symptoms
- Pain at the top/front of the shoulder
- Worse across the chest, overhead, or lying on it
- Localised tenderness; clicking or snapping
Examination
- Tenderness localised over the AC joint
- Pain on cross-chest compression
- Overlapping conditions assessed
Diagnosis
- X-ray – bone loss, cysts and erosions at the outer clavicle
- MRI – bone oedema and other shoulder problems
Example imaging in DCO:

X-ray — Osteolysis

MRI — Osteolysis

MRI — Normal, for comparison
Treatment Options: A Shared Decision
I will discuss all available treatment options with you, explaining the benefits and risks of each. Your preferences, values, and lifestyle will be considered as we work together to create a treatment plan best suited to your needs — this shared decision-making process ensures you are fully informed and involved in your care.
Treatment Depends On
- Your training and occupational demands
- Severity of the bone changes
- Response to activity modification
- Willingness to adapt technique
Good News
DCO often settles when the offending load is modified — many people improve without surgery.
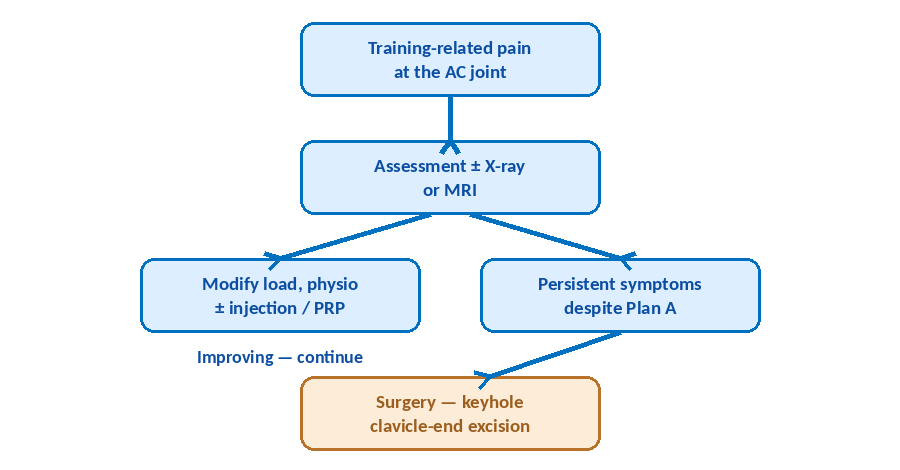
Plan A — Non-Surgical
Many people improve with:
- Rest: and modification of aggravating lifts
- Pain Control: regular painkillers for symptom relief
- Physiotherapy: stretching and strengthening exercises
- Injections: guided cortisone; PRP to promote natural repair
Plan B — Surgical
Considered when…
- Persistent Pain: despite appropriate non-surgical care
- Daily Life: symptoms affecting training or work
- Operation: arthroscopic excision of the distal clavicle
- Approach: keyhole removal of the worn bone end, sometimes may need open excision
- Details: explained fully in a separate leaflet
- The Procedure: known as Arthroscopic Distal Clavicle Excision, this keyhole procedure removes the damaged outer few millimetres of the collarbone so bone no longer grinds on bone. A separate leaflet will be provided for the surgery.
Management Pathway
Red Flags — When to Seek Urgent Help
A hot, swollen joint with fever, or rapidly worsening pain — seek urgent assessment.
If you experience any of the above, contact the practice, your GP, NHS 111, or attend your nearest Emergency Department.
Important Things to Remember
- DCO is an overuse condition – load matters
- Many people improve without surgery
- Technique and training changes are part of treatment
- Doing nothing is always an option
Questions You May Wish to Ask
- What treatments should I try first?
- How long should I try them for?
- What improvement can I expect?
- What happens if I don't have surgery?
Book or Enquire Directly at Each Site
| LIPS Healthcare London | 0203 870 9996 | singh.admin@lips.org.uk |
| Spire Alexandra Chatham | 01634 662866 | alexandraselfpaypsc@spirehealthcare.com |
| Practice Plus Gillingham | 01634 969045 | Private.gillingham@practiceplusgroup.com |