FROZEN SHOULDER (ADHESIVE CAPSULITIS)
This leaflet provides general information to help you understand frozen shoulder and the available treatment options.
Not everyone with frozen shoulder needs surgery.
At the heart of my practice is Shared Decision-Making. Whether we pursue conservative management (Plan A) or surgical intervention (Plan B), the goal is to create a tailored treatment plan that aligns with your lifestyle, values, and functional goals.
This leaflet provides general information and does not replace individual medical advice.
The Anatomy of the Shoulder Joint
The shoulder is one of the most complex joints in the body, relying on several structures working together.
How the Shoulder Works
Three main bones form the joint:
- Humerus (upper arm bone)
- Clavicle (collarbone)
- Scapula (shoulder blade)
The Four Key Joints
- Glenohumeral Joint – the main ball-and-socket joint
- Acromioclavicular (AC) Joint – collarbone meets shoulder blade
- Subacromial Space – tunnel above the rotator cuff
- Scapulothoracic Joint – shoulder blade glides over rib cage
The "Cushioning" (Articular Cartilage)
A smooth, slippery coating on the ball and socket surfaces that lets the bones glide over each other without friction, for pain-free movement.
The Labrum (Stabilising Ring)
A rim of rubbery tissue that deepens the shallow shoulder socket — like a "bumper" or suction cup that keeps the joint stable and prevents dislocation.
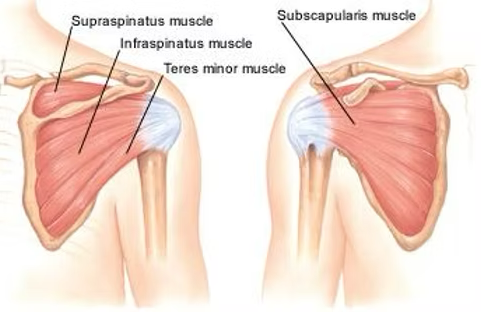
The Rotator Cuff
Four deep muscles keep the ball centred in the socket and let you lift and rotate your arm:
- Supraspinatus
- Infraspinatus
- Subscapularis
- Teres Minor
What Is Frozen Shoulder?
Frozen shoulder (adhesive capsulitis) is a condition in which the shoulder becomes painful and stiff because the joint lining (capsule) becomes inflamed, thickened and tight. It is not dangerous, and in most people it improves on its own — although recovery can take many months.

The Three Stages
Frozen shoulder usually develops gradually and improves over time:
- Freezing (2–9 months) – increasing pain, often worse at night
- Frozen (4–12 months) – pain eases but stiffness dominates
- Thawing (12–24 months) – movement gradually returns
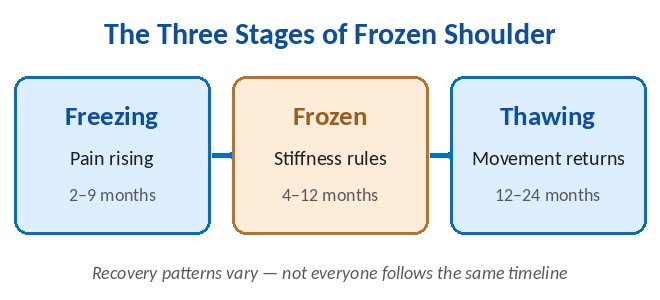
Recovery patterns vary — not everyone follows the same timeline
What Causes It?
The capsule becomes inflamed and tight. It may:
- Start without any clear cause
- Follow a minor injury or jolt to the shoulder
- Develop after surgery or a period of immobility
- Be more common with diabetes or thyroid problems
Symptoms and Examination
Symptoms
- Pain, often worse at night
- Increasing stiffness of the shoulder
- Very limited movement in all directions
Examination
- Movement checked in all directions
- Loss of rotation is typical
- Other causes of a stiff shoulder excluded
Diagnosis
- Usually a clinical diagnosis – history and examination
- Scans only to rule out other shoulder problems
Understanding frozen shoulder — pain typically peaks first, with stiffness following:

Treatment Options: A Shared Decision
I will discuss all available treatment options with you, explaining the benefits and risks of each. Your preferences, values, and lifestyle will be considered as we work together to create a treatment plan best suited to your needs — this shared decision-making process ensures you are fully informed and involved in your care.
Treatment Depends On
- Stage of the condition
- Severity of pain and stiffness
- Your general health (e.g. diabetes)
- Your goals and daily demands
Good News
Frozen shoulder usually improves over time — surgery is rarely needed, although recovery can take many months.
Plan A — Non-Surgical
Many people improve with:
- Pain Control: regular painkillers or prescribed pain relief
- Physiotherapy: gentle exercises to maintain movement
- Injection: steroid injection, often helpful early for pain
- Time: the condition usually settles by itself
Plan B — Surgical
Considered when…
- Severe Symptoms: pain or stiffness remains severe
- No Progress: symptoms persist despite non-surgical care
- Diabetes: results can be less predictable
- Timing: decided together at review
- Details: explained fully in a separate leaflet
- The Procedure: options include Hydrodilatation or Arthroscopic Capsular Release — stretching the tight capsule with fluid, or releasing it with keyhole surgery. Both aim to restore movement. A separate leaflet will be provided for any procedure.
Management Pathway

Red Flags — When to Seek Urgent Help
A hot, swollen shoulder with fever or feeling generally unwell may indicate infection — seek urgent assessment.
If you experience any of the above, contact the practice, your GP, NHS 111, or attend your nearest Emergency Department.
Important Things to Remember
- Frozen shoulder usually improves over time
- Recovery can take many months
- Surgery is rarely needed
- Some stiffness may remain
Questions You May Wish to Ask
- What treatments should I try first?
- How long should I try them for?
- What improvement can I expect?
- What happens if I don't have surgery?
Book or Enquire Directly at Each Site
| LIPS Healthcare London | 0203 870 9996 | singh.admin@lips.org.uk |
| Spire Alexandra Chatham | 01634 662866 | alexandraselfpaypsc@spirehealthcare.com |
| Practice Plus Gillingham | 01634 969045 | Private.gillingham@practiceplusgroup.com |