SHOULDER ARTHRITIS
This leaflet provides general information to help you understand shoulder arthritis and the available treatment options.
Not everyone with shoulder arthritis needs surgery.
At the heart of my practice is Shared Decision-Making. Whether we pursue conservative management (Plan A) or surgical intervention (Plan B), the goal is to create a tailored treatment plan that aligns with your lifestyle, values, and functional goals.
This leaflet provides general information and does not replace individual medical advice.
The Anatomy of the Shoulder Joint
The shoulder is one of the most complex joints in the body, relying on several structures working together:
How the Shoulder Works
Three main bones form the joint:
- Humerus (upper arm bone)
- Clavicle (collarbone)
- Scapula (shoulder blade)
The Four Key Joints
- Glenohumeral Joint – the main ball-and-socket joint
- Acromioclavicular (AC) Joint – collarbone meets shoulder blade
- Subacromial Space – tunnel above the rotator cuff
- Scapulothoracic Joint – shoulder blade glides over rib cage
The "Cushioning" (Articular Cartilage)
A smooth, slippery coating on the ball and socket surfaces that lets the bones glide over each other without friction, for pain-free movement.
The Labrum (Stabilising Ring)
A rim of rubbery tissue that deepens the shallow shoulder socket — like a "bumper" or suction cup that keeps the joint stable and prevents dislocation.
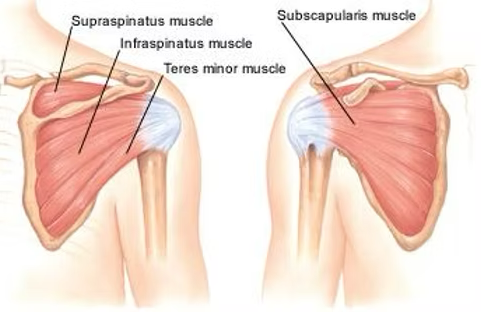
The Rotator Cuff
Four deep muscles keep the ball centred in the socket and let you lift and rotate your arm:
- Supraspinatus
- Infraspinatus
- Subscapularis
- Teres Minor
What Is Shoulder Arthritis?
Shoulder arthritis is a degenerative "wear-and-tear" condition in which the smooth cartilage covering the ball and socket gradually wears away, eventually leading to bone-on-bone contact. It most commonly affects the main ball-and-socket (glenohumeral) joint.
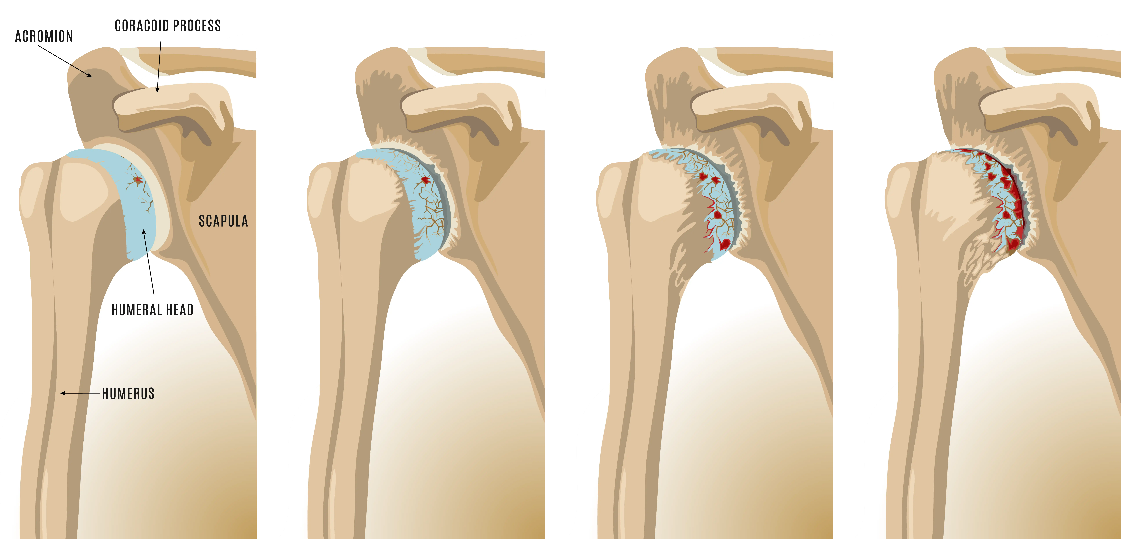
Main Causes
Several conditions can lead to loss of cartilage:
- Osteoarthritis – "wear-and-tear", the most common cause
- Rheumatoid arthritis – inflammatory and autoimmune
- Post-traumatic – years after a fracture or dislocation
What Causes It?
Two further important causes:
- Cuff tear arthropathy – long-standing large cuff tears
- Avascular necrosis – reduced blood supply to the ball
- Linked to injury, steroid use or heavy alcohol intake
- Often several factors combine
Symptoms & Examination
Symptoms
- Deep ache, worse with activity or cold weather
- Stiffness – difficulty reaching back or overhead
- Grinding, clunking or catching (crepitus)
Examination
- Movement and crepitus assessed
- Strength and cuff function tested
- Other causes of shoulder pain excluded
Diagnosis
- X-rays – joint-space narrowing, spurs, deformity
- CT or MRI – surgical planning and soft tissues
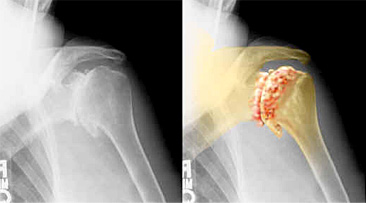
Example X-ray showing an arthritic shoulder
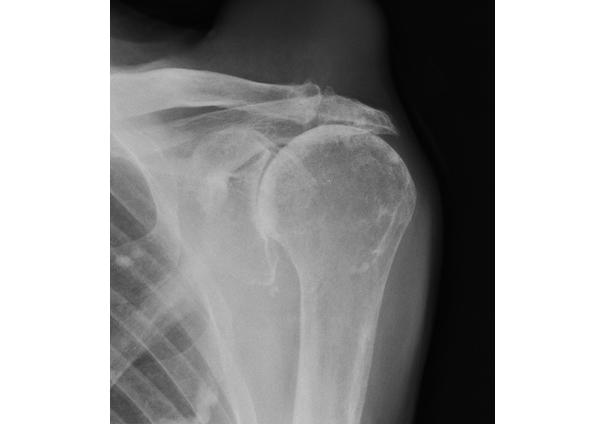
Example X-rays showing an arthritic shoulder:
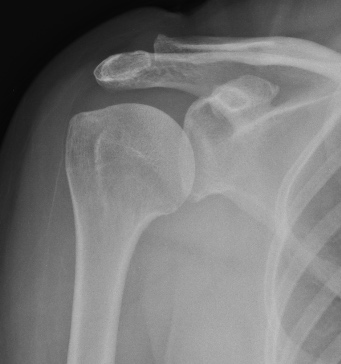
Cuff Tear Arthropathy
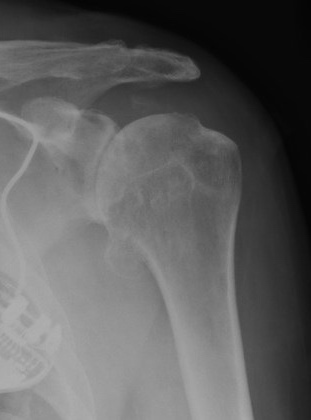
Osteoarthritis

Normal
Treatment Options: A Shared Decision
I will discuss all available treatment options with you, explaining the benefits and risks of each. Your preferences, values, and lifestyle will be considered as we work together to create a treatment plan best suited to your needs — this shared decision-making process ensures you are fully informed and involved in your care.
Treatment Depends On
- Severity of pain and disability
- Stage of arthritis on X-ray
- Cuff function and bone quality
- Your goals and general health
Good News
We treat the patient, not the X-ray — if your pain is manageable, it is perfectly safe to monitor without surgery.
Plan A — Non-Surgical
Most patients begin here
- Activity: modify painful tasks and pace yourself
- Pain Control: regular painkillers; supplements may help some people
- Physiotherapy: maintain movement and function – allow 12 weeks
- Injection: ultrasound-guided cortisone for relief
Plan B — Surgical
Considered when…
- Keyhole "Tidy-Up": removing inflamed tissue, smoothing surfaces
- Cartilage Regrowth: bone-marrow cell technique in selected patients
- Replacement: hemiarthroplasty, anatomic total, or reverse
- Reverse: used when the rotator cuff no longer functions
- Timing: when pain and disability are advanced
- The Procedure: shoulder replacement resurfaces or replaces the worn joint. The type — Hemiarthroplasty, Anatomic Total, or Reverse — is matched to your cuff function and bone quality. A separate leaflet will be provided for the surgery.
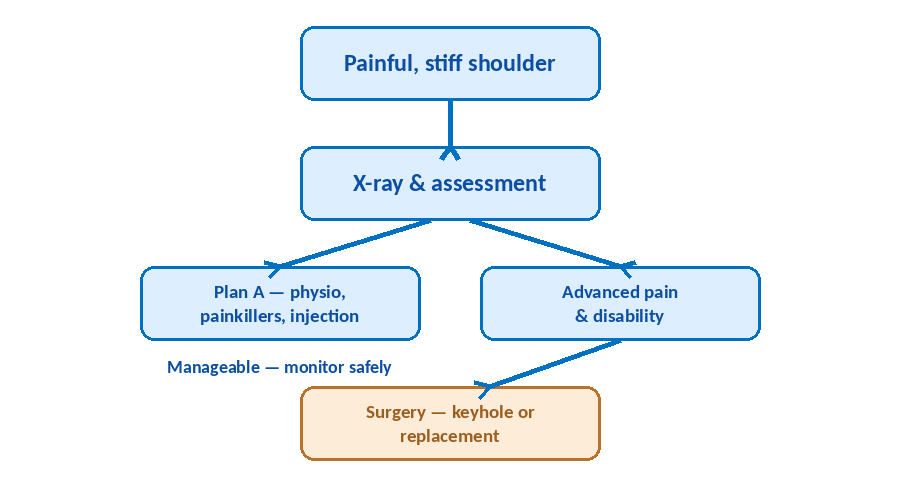
Management Pathway
Red Flags — When to Seek Urgent Help
A hot, swollen joint with fever, or rapidly worsening pain — seek urgent assessment.
If you experience any of the above, contact the practice, your GP, NHS 111, or attend your nearest Emergency Department.
Important Things to Remember
- Scans aren't everything – we treat the patient
- Physiotherapy takes time (often 12 weeks)
- Doing nothing is safe if pain is manageable
- Treatment decisions are individual
Questions You May Wish to Ask
- What treatments should I try first?
- How long should I try them for?
- What improvement can I expect?
- What happens if I don't have surgery?
Book or Enquire Directly at Each Site
| LIPS Healthcare London | 0203 870 9996 | singh.admin@lips.org.uk |
| Spire Alexandra Chatham | 01634 662866 | alexandraselfpaypsc@spirehealthcare.com |
| Practice Plus Gillingham | 01634 969045 | Private.gillingham@practiceplusgroup.com |