RECURRENT DISLOCATION / SHOULDER INSTABILITY
This leaflet provides general information to help you understand shoulder instability and the available treatment options.
Not everyone with shoulder instability needs surgery.
At the heart of my practice is Shared Decision-Making. Whether we pursue conservative management (Plan A) or surgical intervention (Plan B), the goal is to create a tailored treatment plan that aligns with your lifestyle, values, and functional goals.
This leaflet provides general information and does not replace individual medical advice.
The Anatomy of the Shoulder Joint
The shoulder is one of the most complex joints in the body, relying on several structures working together:
How the Shoulder Works
Three main bones form the joint:
- Humerus (upper arm bone)
- Clavicle (collarbone)
- Scapula (shoulder blade)
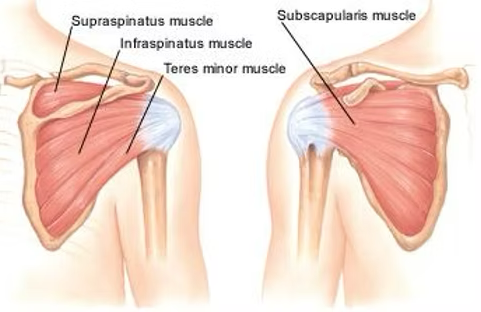
The Labrum (Stabilising Ring)
A rim of rubbery tissue that deepens the shallow shoulder socket — like a "bumper" or suction cup that keeps the joint stable and prevents dislocation.
The Rotator Cuff
Four deep muscles keep the ball centred in the socket and let you lift and rotate your arm:
- Supraspinatus
- Infraspinatus
- Subscapularis
- Teres Minor
The Four Key Joints
- Glenohumeral Joint – the main ball-and-socket joint
- Acromioclavicular (AC) Joint – collarbone meets shoulder blade
- Subacromial Space – tunnel above the rotator cuff
- Scapulothoracic Joint – shoulder blade glides over rib cage
The "Cushioning" (Articular Cartilage)
A smooth, slippery coating on the ball and socket surfaces that lets the bones glide over each other without friction, for pain-free movement.
What Is Shoulder Instability?
After a dislocation, the soft tissues that normally stabilise the joint — including the labrum — can be stretched or torn and may not heal fully. This can leave the shoulder feeling unstable, and in some people it may dislocate again with minimal force.

Who Is at Risk?
Instability is more common in:
- Younger patients – especially under 20
- Men / Boys
- Contact and overhead sports
- Naturally flexible (hypermobile) joints
What Causes It?
After a shoulder dislocation:
- The stabilising tissues stretch or tear
- The labrum can be pulled off the socket
- Healing may be incomplete
- Recurrence risk is highest in the young
Symptoms & Examination
Symptoms
- Repeated dislocations or partial slips (subluxations)
- A feeling the shoulder may "give way"
- Reduced confidence using the arm overhead
Examination
- Apprehension and stability tests
- Range of movement and strength
- Generalised joint laxity assessed
Diagnosis
- X-rays to check for bone injury
- MRI arthrogram for soft tissues; CT for bone loss
Example MRI images assessing the shoulder:
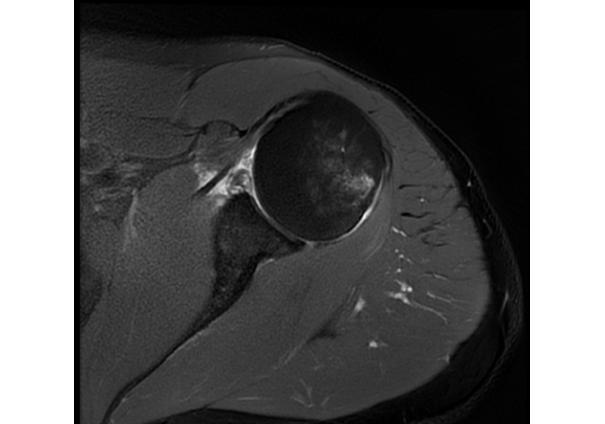

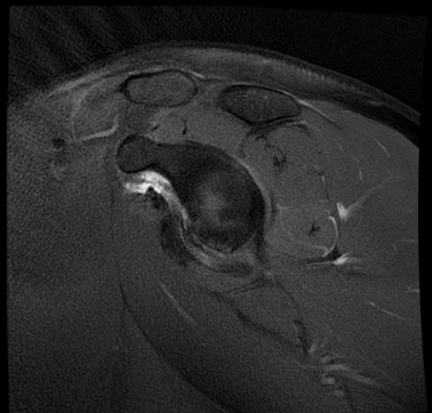
Bankart Tear
Treatment Options: A Shared Decision
I will discuss all available treatment options with you, explaining the benefits and risks of each. Your preferences, values, and lifestyle will be considered as we work together to create a treatment plan best suited to your needs — this shared decision-making process ensures you are fully informed and involved in your care.
Treatment Depends On
- Number of dislocations
- Your age and sport
- Bone loss and soft-tissue damage
- Response to rehabilitation
Good News
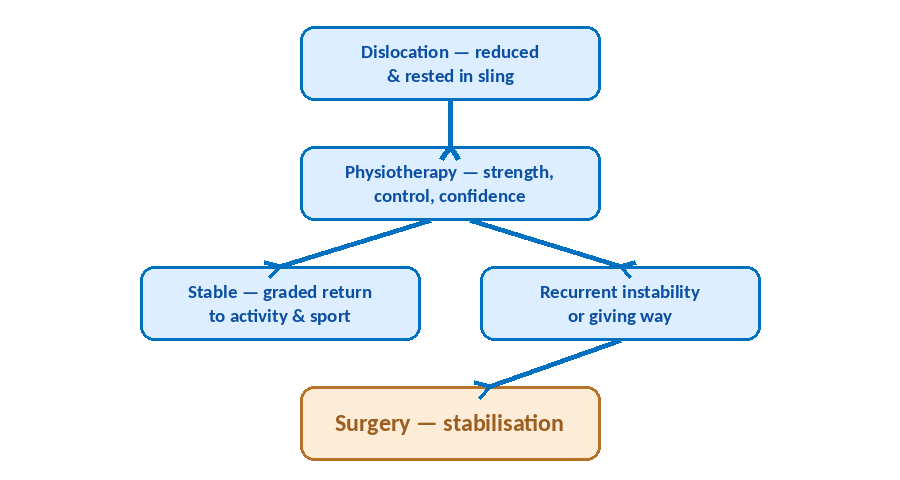
Many shoulders regain stability with rehabilitation alone — surgery is reserved for shoulders that keep dislocating or giving way.
Plan A — Non-Surgical
After a first dislocation
- Sling: a short period of rest
- Pain Control: regular painkillers or prescribed pain relief
- Physiotherapy: restore movement, strength and control
- Return: graded return to activity and sport
Plan B — Surgical
Considered when…
- Recurrence: the shoulder keeps dislocating or feels unstable
- Function: symptoms affect daily activities or sport
- Rehab: non-surgical treatment has not been successful
- Approach: keyhole or open stabilisation
- Details: explained fully in a separate leaflet
- The Procedure: stabilisation surgery repairs or reinforces the damaged stabilising tissues, by keyhole or open technique depending on the damage and any bone loss. A separate leaflet will be provided for the surgery.
Management Pathway
Red Flags — When to Seek Urgent Help
A dislocated shoulder that has not been put back in place, or numbness, tingling or a cold hand after a dislocation — attend emergency care immediately.
If you experience any of the above, contact the practice, your GP, NHS 111, or attend your nearest Emergency Department.
Important Things to Remember
- Not every unstable shoulder needs surgery
- Recurrence risk is highest in young, active patients
- Rehabilitation is the foundation of treatment
- Treatment decisions are individual
Questions You May Wish to Ask
- What treatments should I try first?
- How long should I try them for?
- What improvement can I expect?
- What happens if I don't have surgery?
Book or Enquire Directly at Each Site
| LIPS Healthcare London | 0203 870 9996 | singh.admin@lips.org.uk |
| Spire Alexandra Chatham | 01634 662866 | alexandraselfpaypsc@spirehealthcare.com |
| Practice Plus Gillingham | 01634 969045 | Private.gillingham@practiceplusgroup.com |